
FUEL ONLINE / Pain Management Marketing / Industry growth plan
Pain Management Marketing Strategy

A pain practice must explain services, locations and appointment access without turning marketing into clinical screening or placing health details in ad tools. Fuel Online's pain management marketing work helps practice owners, administrators and marketing directors turn that distinction into accurate offers and contact routes for reviewed service information, provider and location discovery, consultation requests and referral pathways. We coordinate website, local, paid and follow-up work, then show which activity produces accepted work.
Location, appointment request and a safe callback method. Keep detailed medical histories out of ordinary marketing forms; route clinical eligibility through approved intake.
Make the access and referral journey part of the marketing brief
A pain management marketing agency should help people understand the practice’s actual service scope and how to contact the appropriate team. Fuel Online can connect that information with search visibility, local presence and measurable inquiry routing. The strongest growth assignment identifies which service and location need demand, then removes ambiguity from the next administrative step.
Start by separating prospective patient inquiries, professional referrals and current patient requests. These audiences arrive with different questions and supporting information. A single general contact form may obscure those differences. The website can offer clear routes while the practice retains control over clinical assessment and the information required through its approved systems.
| Audience | Useful public information | Handoff to evaluate |
|---|---|---|
| Prospective patient | Approved services, locations and appointment request process | Inquiry reaches the correct scheduling team |
| Referring professional | Current referral contact and submission instructions | Referral is received and acknowledged |
| Existing patient | Clearly identified current patient route | Request avoids the acquisition workflow |
The most useful content often addresses practical uncertainty. Explain which office a page describes, how a person requests contact and what the team will clarify next. If a referral is needed for a particular pathway, publish only the practice’s verified current instructions. Avoid making broad administrative statements that staff cannot keep accurate across services and locations.
Service explanations should establish relevance using clinician-approved language. Pair them with genuine team information and a clear appointment route. Marketing does not need to promise relief or recommend a particular intervention to be persuasive. A precise description of the practice and a dependable response process can make the organization easier to evaluate.
A referral checklist can also reduce repeat administrative calls when it reflects the actual receiving process. Assign an owner to review it whenever the practice changes how referrals arrive or how offices share responsibility.
Choose the acquisition constraint to solve first
A practice with weak local discovery may need accurate office information and stronger service architecture. One with many misdirected contacts may need clearer page boundaries. Another may receive appropriate referrals but struggle to acknowledge them efficiently. Each condition calls for a different agency deliverable, even when all three appear in a dashboard as low conversion.
Ask the agency to demonstrate one complete journey: the search or referral question, the page that answers it, the contact route and the receiving team’s disposition. Include an information owner inside the practice. Without that ownership, service descriptions and access instructions can drift as operations change.
Campaign expansion should follow operational readiness. A new service campaign requires an accurate public offer, an appropriate destination and staff who recognize the inquiries it produces. The agency should explain how it will distinguish growth demand from current patient service requests. Increasing contact volume without that distinction creates a poor basis for budget decisions.
Measure the quality of the administrative handoff
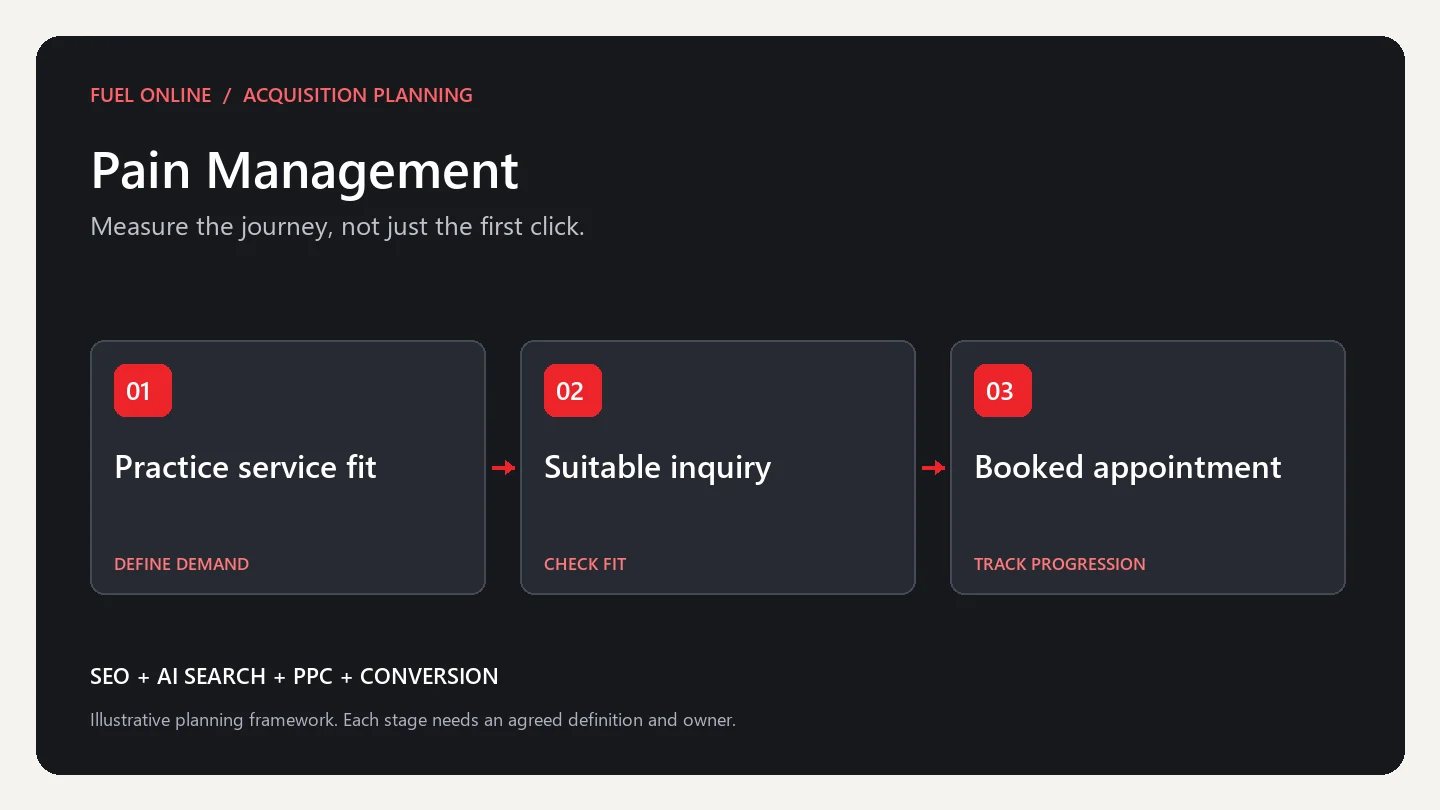
Review inquiries, successful contact, appointments arranged and first appointments attended as separate observed stages. For referrals, distinguish received, incomplete, acknowledged and scheduled using the practice’s own definitions. Aggregate reporting can reveal where a handoff breaks without transferring individual clinical details into routine marketing tools.
Loss reasons should be actionable and limited. Wrong office, service outside scope and inability to reach a contact suggest different fixes. They should not become a marketing team’s clinical judgment. The practice determines what information is appropriate to collect and how its staff should handle it.
For a pilot, improve one service-location journey and review it with the receiving team. Record the content and routing changes alongside availability changes. Use the findings to decide whether the next investment belongs in visibility, page clarity or follow-up. This keeps the growth discussion tied to observable work rather than promises about treatment outcomes.
Explore medical practice marketing and the related orthopedic marketing framework. Fuel’s scope should state the service, audience, access route and commercial decision the reporting will support.
Test referral maintenance before expanding the campaign
Give finalists the practice's approved public referral instructions and ask them to show how a future correction would be handled. Use an illustrative change to the receiving contact or administrative route, without inventing clinical requirements. The response should identify the source owner, affected resources, implementation responsibility, and verification result. A referral page is an operational asset that needs a maintenance process, not simply another piece of search content to publish once.
Ask the agency to distinguish the public explanation from the systems used to submit and handle individual information. The marketing team can organize approved instructions and inspect an appropriate test route. It should not determine what an individual referral clinically requires or move sensitive details into a routine marketing report. The practice should name the owners who confirm the actual administrative process and the boundaries of the agency's access.
Use an ambiguity register for unresolved instructions
Record conflicting public statements with the affected destination and the person authorized to resolve them. An example might involve two pages naming different receiving routes. The team should preserve the observations until the practice confirms the current instruction, rather than assume the most prominent resource is correct. The record should show the approved replacement and which connected assets require review.
Track requested, implemented, and verified work separately. Another system owner may need to complete part of the correction. A request sent to that person is not evidence that the public route now behaves as intended. Ask a staff member outside the launch team to use the record to find the current source and next action. This tests whether the process can survive an account or staffing change without reintroducing an old instruction.
Define the evidence needed for acceptance
Use agreed fictional nonclinical scenarios with the receiving team to inspect the intended path. Label test activity clearly. Confirm the message shown to the user, destination, and relevant context available to staff within the approved test arrangement. Include an incomplete or wrong-office scenario where relevant. A confirmation screen is not proof that the correct operational workflow completed, and a received item is not proof that every subsequent stage occurred.
The acceptance pack should contain the approved reference, final resources, test results, unresolved dependencies, and update owners. Separate strategy recommendations from implemented changes. The buyer should know whether the agency supplies a plan, approved copy, publication, and checks, or only some of those activities. This gives the practice a concrete basis for comparing proposals and avoids treating a completed presentation as a completed access improvement.
Make the next decision specific
At review, distinguish a factual information gap, a broken route, and later operational activity. Those require different actions. A clearer instruction can be verified promptly, while patterns in requests and scheduling need observation and may have other influences. The report should explain which conclusion the evidence supports and what remains uncertain. The next investment should address the most consequential verified constraint, leaving a maintained referral and access process instead of more disconnected content.
AGGRESSIVE FROM THE START
One month. The work many agencies stretch across three.
Our mandate: move faster, go deeper and put experienced specialists to work immediately.
Fuel attacks the work in parallel: site audits, technical errors, new content, internal links, backlink outreach and conversion improvements. Your agreed scope determines the channels; urgent fixes do not wait behind a drawn-out planning phase.
The pain management marketing brief identifies visibility and lead barriers. Actionable fixes move into production while deeper analysis continues.
Your marketing agency for pain management practices work runs alongside industry-specific content, relevant links and earned-authority outreach, based on your agreed scope.
The marketing strategy for pain management practices review shows completed work, lead quality and the next opportunities. You see who owns each action.
Fast execution is the operating standard. Access, approvals and scope shape delivery; search and revenue results have their own timelines.
Pain management marketing for real buyer decisions
Marketing for a pain management practice has to account for a core operating distinction. A prospective patient needs to understand available services and how to request an appointment; clinical eligibility, diagnosis and treatment choice remain inside the practice’s approved process. Fuel Online turns that difference into offer, audience and journey decisions rather than a broad awareness plan.
The first map connects prospective patients, caregivers and referring professionals seeking an appropriate location or service to reviewed service information, provider and location discovery, consultation requests and referral pathways. Each route states the buyer question, information needed to assess fit, proof the organization can support and the next human handoff. For the owner or marketing lead, choosing a marketing agency for pain management practices means making this buyer distinction visible before contact.
Deliverables from a marketing agency for pain management practices
The engagement produces a buyer-and-offer matrix, page and campaign priorities, a channel role plan, qualification rules, measurement definitions and a opening execution sprint implementation sequence. For pain management practice marketing, those deliverables are built from location, requested appointment or service at a nonclinical level, referral requirements, preferred callback method and appointment availability and current provider schedules, new-patient availability, referral rules and staffed callback coverage.
Work begins by correcting offer, location and availability facts. The next step repairs the highest-value page and handoff. Media or content expands only after the receiving team can record why inquiries are accepted, redirected or declined. A marketing agency for pain management practices scope is inspectable when the owner, dependency and release check are named.
- Buyer and offer map separating reviewed service information, provider and location discovery, consultation requests and referral pathways.
- The plan for marketing agency for pain management practices includes channel roles and investment rules tied to provider schedules, new-patient availability, referral rules and staffed callback coverage.
- Use marketing strategy for pain management practices reporting to document handoff and scorecard showing which activity produces accepted work.
Illustrative marketing strategy for pain management practices decision path
Illustrative example, not a client result: compare a prospective patient looking for the nearest available consultation with a referring office comparing locations and referral steps.
The decision is how the marketing plan separates location, service fit, reviewed clinical information, scheduling capacity and the appropriate handoff before either buyer reaches the same report or handoff. Use pain management marketing to assign a channel role and next action to each path. A provider acting as a marketing agency for pain management practices should show which route changes first, while marketing strategy for pain management practices should explain how that choice responds to accepted and rejected demand.
Classify the demand
Compare the illustrative queries "pain management consultation [city]" and "pain clinic referral requirements". Confirm that each describes work you offer in a market and time frame your team can support. The phrases are examples, not measured-volume claims.
Build the appropriate path
For pain management practice marketing, give each buyer a different page, channel role and response rule. Use verified clinician credentials, reviewed service explanations, accurate locations, appointment process and approved patient resources only when your organization can verify and approve it.
Record the commercial outcome
Retain the source, chosen path and receiving decision. Record why an inquiry advanced or stopped so the next change responds to actual fit instead of increasing activity blindly.
A pain management marketing diagnostic for marketing strategy for pain management practices: symptom to decision
Use this framework when appointment requests grow while service fit, referral needs, location capacity and safe callback ownership remain unclear. The pain management diagnostic turns that concern into an inspection the owner, marketing lead and receiving team can review together.
Trace the visible pain management buyer path against current operating capacity. The review should end with one bounded change, its owner and the evidence needed to keep, correct or stop it.
- Retain one observable example and its receiving consequence.
- Connect the source, page or campaign to the response record.
- Use marketing strategy for pain management practices to state the bounded change and the evidence for the next decision.
Name the observable symptom
For pain management marketing, the warning sign is that channels present different offers or next steps for the same buyer. Record one recent example and the business consequence rather than starting with a channel-wide assumption.
Inspect the path
Review the requested location and service at a nonclinical level, referral context, callback disposition, appointment availability and attendance. For the marketing layer, inspect the offer map, priority pages, channel roles, local profiles and handoff ownership. Keep the source, promise, handoff and disposition together so the failure point is visible.
Make a bounded decision
The industry rule is to change the page or route when a service, provider, location or referral path requires a different approved next step. For this marketing decision, choose one buyer path to correct across the website, local visibility, paid activity and follow-up. Name the owner, dependency and release check before implementation.
Require an inspectable output
The output is a buyer-and-offer map, channel decision table and prioritized implementation backlog. It should show what changed, why it changed and what receiving outcome will determine whether the team keeps, corrects, expands or pauses the work.
Measurement standards for pain management marketing and a marketing agency for pain management practices
For pain management practice marketing, channel reach, engagement and response activity help explain what changed, but they do not establish commercial value alone. The shared scorecard follows eligible inquiries, scheduled consultations, attended appointments, and location capacity and segments them by service, location, buyer path and source where the organization can do so responsibly.
The review also examines provider schedules, new-patient availability, referral rules and staffed callback coverage. Reporting should record attribution gaps, offline outcomes and why pain management inquiries were declined. Each review should close with a decision to keep, correct, expand, pause or investigate a specific page, campaign, answer or handoff. Measurement from a marketing agency for pain management practices should keep rejection reasons beside accepted outcomes.
How to compare a marketing agency for pain management practices on marketing strategy for pain management practices
Ask how channel priorities change when service mix or capacity changes. Before selecting a provider for pain management marketing, require the proposal to name the first deliverables, working team, required access, client inputs, review cadence and dependencies. It should state which pain management practice evidence the organization must substantiate and who approves it.
Request a sample decision log that shows what changed after an accepted or rejected inquiry. Confirm account, content and data ownership. Reject a provider that ignores agreed service or territory exclusions, promises a guaranteed outcome or cannot explain the next concrete decision. A credible marketing agency for pain management practices provider can apply the method to one current page, campaign, answer or handoff.
When reviewing marketing strategy for pain management practices, ask the provider to show the first decision it would make from one current buyer path and the evidence required to make it.
A decision log for marketing strategy for pain management practices should connect one released change to the reason an inquiry advanced or stopped.
How we measure marketing strategy for pain management practices
- eligible inquiries
- scheduled consultations
- attended appointments
- location capacity
Separate inquiry volume from usable demand
Qualified-inquiry rate = inquiries meeting your agreed criteria ÷ total inquiries reviewed.
Illustrative arithmetic: 20 suitable inquiries out of 50 reviewed inquiries is a 40% qualified-inquiry rate. Record why the other 30 did not fit before increasing investment.
Agree on the baseline, data source and qualification criteria before comparing results. Separate visibility from inquiries and accepted business opportunities.
CONNECTED SERVICES
Choose the right next step for your business
Explore Fuel’s Industry growth plan capabilities, published campaign work and team to evaluate how we would support your organization.
BEFORE YOU CHOOSE AN AGENCY
Questions about marketing strategy for pain management practices
What should pain management marketing include?
Expect a buyer-and-offer map, channel roles, page and campaign priorities, a handoff plan and a scorecard for reviewed service information, provider and location discovery, consultation requests and referral pathways. The proposal should identify owners, dependencies, implementation access and the evidence the pain management team must approve. It should also explain how changes in provider schedules, new-patient availability, referral rules and staffed callback coverage affect priorities. Use the release checklist to verify completed work and whether the intended buyer reached the correct handoff.
How should work with a marketing agency for pain management practices be phased?
For marketing agency for pain management practices, the first useful milestone is an agreed offer map and one repaired buyer-to-handoff path. Delivery speed depends on access, approvals and provider schedules, new-patient availability, referral rules and staffed callback coverage. Set release checks and review dates before implementation begins. Assess released work first, early response second and downstream business movement only after enough demand and operating time exist to interpret it. Phase marketing agency for pain management practices around one released buyer path, its acceptance check and the next evidence-based decision.
What does our team provide for marketing strategy for pain management practices?
For marketing strategy for pain management practices, bring current service and location facts, examples of suitable and unsuitable inquiries, current capacity constraints and access needed for marketing. Name the reviewer who can approve pain management service details, media and evidence. Health details remain in the practice or clinic approved system. Share only the fields needed to make marketing and handoff decisions.
How do we compare pain management marketing providers?
Ask the agency to explain how it would handle a prospective patient looking for the nearest available consultation differently from a referring office comparing locations and referral steps. Its answer should connect one pain management page, campaign, source or routing change to the required input and receiving outcome. Confirm account and data ownership. When evaluating providers, treat generic activity lists, invented proof and reports that count every inquiry equally as warning signs. Ask what marketing agency for pain management practices will deliver first and how marketing strategy for pain management practices will change after an accepted or rejected inquiry.
Make your next agency conversation specific.
Bring the services, locations and appointment paths your practice wants clarified. Fuel Online can turn those inputs into a buyer-path and channel-priority brief through a focused pain management marketing engagement, with the first owner, release check and success signal clearly named.
Talk with a Fuel strategist →